Tuesday, July 11, 2023

A Narrative Review of the Impact of Healthy Nutrition and Regular Exercise on Physical and Mental Wellness


A Narrative Review of the Impact of Healthy Nutrition and Regular Exercise on Physical and Mental Wellness

Introduction

According to the World Health Organization (2017), being healthy is not defined as the absence of disease, but as a state of complete physical, mental and social well-being [1]. In this description, it is seen that health is considered to be multifactorial and well-being is underlined. It is not always possible or easy to be healthy in all areas of life due to hereditary and environmental factors, but it is emphasized that healthy living habits can be preventive for diseases [2]. Behaviors that serve to protect and increase the well-being of individuals are defined as healthy lifestyle behaviors [3]. These behaviors include responsibilities such as adequate and balanced eating habits, stress management, regular physical activity, cognitive development, and sociological development [4]. To live a healthy life and to minimize the health risks that may occur in aging, the main factors are nutrition and physical activity [5] emphasize that inadequate exercise or inactive life is a real cause of chronic diseases and death. Physical inactivity has been associated with the development of 40 chronic diseases and premature death, including major non-communicable diseases such as type 2 diabetes and coronary heart disease [6]. Blair et al. 1989 stated that cardiorespiratory condition, generally measured by maximum oxygen uptake (VO2max), is an important determinant of health. [7], showed in exercise tests that for every 1 metabolic equivalent increase, there is a 12% improvement in survival.

Exercise improves multiple factors that affect VO2max, including oxygen-carrying capacity, oxygen diffusion to working muscles, and adenosine triphosphate production [8]. Another main component of a healthy life is nutrition. A healthy diet with the appropriate balance of nutrients can prevent or delay the development and complications of not only common chronic diseases such as diabetes, high blood pressure, heart disease, and cancer but also diseases [9]. Healthy aging, maintenance of function, immunity, and healing are supported by a high-quality diet that meets micronutrients (vitamin C, A, D, E, and K; zinc; folate; calcium; iron; and B vitamins) and macronutrients (protein, carbohydrate, and fat) requirements [10]. No single food contains all the nutrients the body needs. There are different types of nutrients in each of the foods that have different properties and have different functions in body functioning [11- 13]. For optimal nutrition, it is necessary to take these nutrients in certain proportions [14,11-13]. The ratios of these nutrients in the diet affect each other’s absorption, metabolism, and requirement [11-13]. In addition, the foods consumed for optimal nutrition do not only contain essential nutrients, but also contain bioactive components called phytochemicals, which are effective in the protection and development of health and the prevention of dietrelated chronic diseases [15-17].

Discussion

Many studies aiming to reveal the importance of exercise for a healthy life have focused on improving health and increasing physical activity. A study of healthy community-dwelling older adults showed that seven to twelve months of regular exercise was associated with changes in self-efficacy and cognitive mediators, and these gains were associated with regular exercise [18]. In another study, self-efficacy was increased for those who completed an exercise prescription scheme, but not for those who left without completing a regular exercise prescription [19]. It has been concluded that positive changes can be achieved on health parameters through the nutrition education program conducted to improve the life health of CVD high-risk groups in socio-economically deprived regions [20]. Since it’s observed that in the school-age and pre-adolescent period, overweight and obesity tends to increase more frequently, it should be important for individuals in this age group to develop healthy living habits together with regular physical activity and healthy nutrition education [21-23].

Conclusion

The most important point to be emphasized about the concept of healthy life is health; not only the absence of illness and disability but also the fact that one lives in a state of complete well-being from a physical, psychological and social point of view. Being healthy all your life is everyone’s dream. In line with this goal, many factors can be mentioned in life to maintain health and become healthier, but among all these factors, a natural and balanced diet and physical activity are of great importance for a healthy life. With a better understanding of the importance and necessity of physical activity for health all over the world, a more active lifestyle and regular exercise have been adopted by the people. With the adoption of an active lifestyle shaped by physical activity, the chances of healthy aging will increase thanks to the preservation and improvement of the physical and psychological health of people of all ages. And with a natural and balanced diet, it is possible to provide all the nutrients necessary for the efficient and effective functioning of the whole body. And also, it is known that in the presence of a balanced diet, the body will be more resistant to all kinds of disease-causing factors, infections, chronic fatigue, and metabolic performance losses and a decrease in the incidence of chronic diseases such as cardiovascular diseases, hypertension, diabetes, depression, osteoporosis will be observed. And so it will be possible to increase the chances of a long and healthy life in the presence of healthy nutrition and regular exercise.


For more Articles on: https://biomedres01.blogspot.com/

Saturday, July 8, 2023

Infection of Piglets with the Porcine Respiratory and Reproductive Syndrome Virus (PRRSV): A Morphological Study


Infection of Piglets with the Porcine Respiratory and Reproductive Syndrome Virus (PRRSV): A Morphological Study

Introduction

The porcine respiratory and reproduction syndrome virus (PRRSV) forms small, enveloped particles (50-65 nm in diameter) harboring a relatively long (approximately 15 kb in size) single strand RNA genome [2]. The viral RNA (vRNA) is a positive-sense molecule with terminal cap at 5´-end and a poly-A repeat at 3´- end [3]. In the course of virus replication, the vRNA is copied as whole, when synthesized via a full length negative-strand RNA intermediate. The vRNA sequence begins with 2 (two) long open reading frames (called ORF1a and ORF1b), which together comprise about 75% of the total genome sequence [4]. This portion of the genome specifies 14 non-structural proteins (nsps) which are formed by cleavage of both translated polyproteins. Of special importance are, for example, two non-structural proteins (nsp9 and nsp12), which function as vRNA replicase, also termed RNAdependent RNA polymerase (RdRp) [5]. The rest of the genome encodes 7 structural proteins, out of which 5 are glycoproteins (designated GP2a/Gp2, GP2b/E, GP3, GP4 and GP5) along with the M (membrane) protein and the N nucleoprotein [6].
Regarding to the structure of the vRNA, the PRRSV has been classified as a member of family Arteriviridae (order Nidovirales), along with the equine arteriitis virus and the lactate dehydrogenase elevating virus of mice [7]. In the course of vRNA replication, a total length (genomic) minus strand is generated, which serves as template for the synthesis of new vRNA molecules. During viral mRNA synthesis, the negative sense RNA sequence is being formed first; then a set of positive sense nested sub genomic (sg) RNA molecules is transcribed. Finally, the full set of minus sense sub genomic (sg) RNAs is formed, which becomes a template for the synthesis of functional positive sense sg mRNAs [7]. Both strands are complementary to each other; the coterminal 3´-ends are equipped with a common leader sequence at their 5´-ends [8,9]. The viral genome reveals several (but at least two) conserved transcription regulatory sequences (TRS), which are located either in the front of ORF1a (encoding the structural protein GP2a) or before ORF2a (encoding the envelope glycoprotein Gp2b/E).
The classical PRRSV strains which were isolated in the US (VR2332) and/or in Europe (Lelystadt) differ at both, by serological as well as genome examinations [10]. Experimental infection with the PRRSV isolates can be lethal in newborn and/ or 3-week-old piglets. A key event of the infection process is the involvement of porcine alveolar macrophages, which are the most important virus target also mediating virus spread [11]. To date, at least two macrophage surface molecules are known as entry mediators: the siglec sialoadhesin and a scavenger receptor CD163 [12]. The PRRSV induced pneumonia is characterized by thickening of inter-alveolar septa due to infiltration with macrophages and by the presence of occasional inflammation and cell debris within the alveoli itself [13]. Also, alveolar pneumocytes of type II may be found PRRSV antigen positive along with the hyperplasia of peribronchial lymphatic tissue [14]. The severity of lung lesions may vary from relatively mild to quite extensive. The viral genotypes can differ in their pathogenicity, namely the Type 2 North American PRRSV induces more severe respiratory disease than type 1 European virus. Nevertheless, mild thickening of interalveolar septum can be mistaken with focal thickening of inter-alveolar septa in combination with slight infiltration of peri-bronchial connective tissue (referred to as mild non-specific interstitial infiltrate, MNSII), was occasionally seen in a proportion of non-infected control piglets and interpreted as unrelated to PRRSV infection [15]. In this paper we describe the correlation of the lung lesions as seen at histological examination slides stained with, HE on comparison to the immunohistochemical detection of viral N-protein along with the results of serological tests for N-protein antibodies.

Materials and Methods

Virus

A North American strain was cultured on the MARC-145 cell line; its titer end point (TCID50) was evaluated using a 96-well plate as described by Zhao, et al. [16] and/or Ramakrishnan (2016) [17].

Animals

Pigs (28 infected animals) were inoculated into both nostrils with 105 TCID50 of above mentioned PRRSV strain administered in a volume of 300μl culture supernatant. The negative control (9) animals were inoculated with a virus free culture medium; these animals were kept under conditions of careful isolation avoiding any contact with the virus-inoculated piglets.

Specimen Sampling and Histological Examination

At given intervals post-infection, the animals were succumbed. Blood was drawn for obtaining serum, whole the tissue samples (coming from each lung lobe, from both tonsils including adjacent paryngeal area, from spleen and liver) were removed and immediately immersed into in 10% neutral formalin for 24hr. Fixed tissue samples were rinsed in phosphate buffer, dehydrated in a series of corresponding reagents and embedded into paraffin as described Szeredi, et al. [18] and/or Stipkovits, et al. [19]. Next to sectioning, the sections were stained either by classical hematoxylin and eosin (HE) and/or treated by immunohistochemical reagents, namely using a commercial anti-PRRSV N-protein antibody mixture SDOW-17 and SR-30 in the first layer. This has been purchased from 4rtilab (SDOW17-A and SR30-A, respectively) and mixed for use in an equal 1:1 ratio.

ELISA Titer Measurements

The specific serum class IgG antibody levels against the PRRSV N antigen were determined using the INgezim PRRS 2.0 ELISA kit (purchaed from Eurofins) strictly following the procedure recommended by the manufacturer.

Saliva Collection

The pooled oral fluid was collected from each animal separately using the Civtest suis oral fluid rope IDEXX. Obtained saliva samples we examined for the presence of class IgA specific antibody to the N-antigen of PRRSV. The antibody test was performed with the Oral Fluids (IDEXX PRRS OF) kit as recommended in the manufacturer’ s manual.

Results

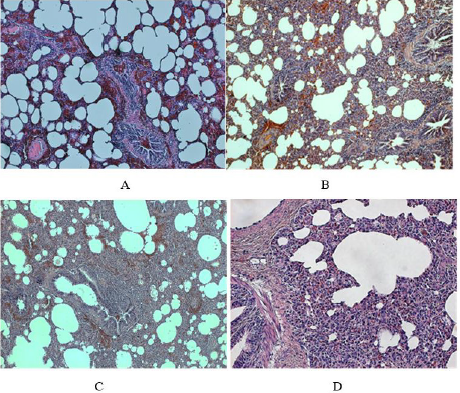
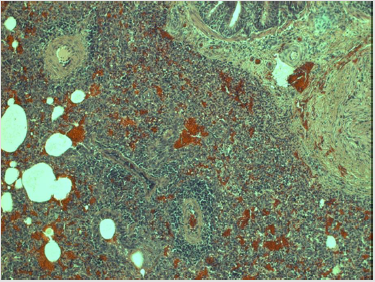
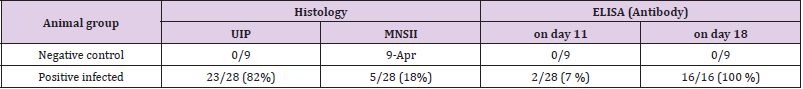
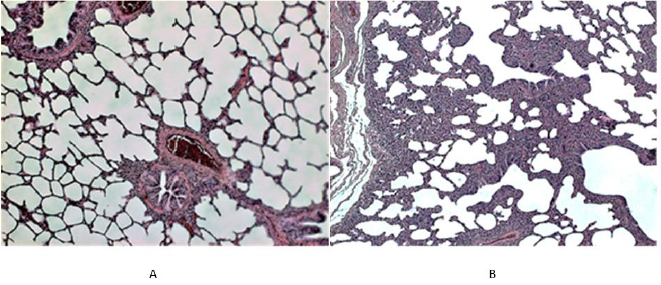
As documented in Figure 1A the interalveolar septi in normal lung tissue are very thin in order to ensure the diffusion of oxygen into blood capillaries, where the erythrocytes circulate. Occasionally, a few mononuclear cells (mainly lymphocytes) might be seen in the peribronchial connective tissue. Surprisingly, in 4 out of 9 uninfected (control) piglets, a slight focal thickening of interalveolar septi was noted along with the accumulation of relatively few interstitial infiltrates consisting of mononuclear cells, mainly lymphocytes (Figure 1B). As expected, staining for the N-antigen of PRRSV in the control lung tissue was negative by all control animals, including the above-mentioned areas in which the above mentioned mild interstitial infiltrate (MNSII) has been detected. The non-extensive MNSII (Figure 2A) has been also found in a few infected piglets (5 out of 28, 18 %), especially when the N-protein could not be detected (Table 1). As expected, in the majority of infected animals (23 out of 28) the lung tissue revealed a typical picture of usual interstitial pneumonia (UIP). In the latter, the interalveolar septi were thicker due to the presence of a rich mononuclear cell infiltrate. In UIP cases, the capillaries were widened along with occasional focal bleeding in result to the injury of endothelial cells (Figures 2B & 2C). High power view of such areas showed that the interstitial infiltrate in question consisted mainly of lymphocytes (Figure 2D). Occasionally (for example in piglet no. 40) the infiltrate was so extensive that it altered the original lung structure (Figure 3).

biomedres-openaccess-journal-bjstr

Figure 1: Histological picture of the lung tissue in uninfected (control) piglets.
A. In the left (piglet no. 5). The normal lung structure at low power view shows thin interalveolar septa devoid of any infiltrate; in the peribronchial (and/or perivascular) connective tissue a few mononuclear cells (mainly lymphocytes) can be seen.
B. In the right (piglet no. 2). Unlike to 1A, this Figure shows areas of thickened interalveolar septa due to the accumulation of monocellular cells (mainly of lymphocytes). Such focal mild non-specific interstitial infiltrate (MNSII) was found in the lungs of 5 out of 9 uninfected controls (Table 1).

biomedres-openaccess-journal-bjstr

Table 1: Survey of histological lesions and the N-antigen presence in infected piglets.

Note: *Mild non-specific interstitial infiltrate (in the peribronchial area and/or interalveolar septa); ** Severe interstitial infiltrate corresponding to the diagnosis of “Usual Interstitial Pneumonia” [1].

biomedres-openaccess-journal-bjstr

Figure 2: Histological findings in the lungs of PRRSV infected piglets.
A. In the left above (piglet no. 16). At low power view some areas of the lung tissue even in the infected animal showed rather less extensive thickening of interalveolar septa (infiltration by mononuclear cells referred to as mild non-specific interstitial infiltrate, MNSII); note the dilatation of small vessels (magn x100).
B. In the right above (piglet no. 16). In contrast to the area shown above, another lung area of the same reveals typical UIP with more widespread thickening of interalveolar septa and their abundant mononuclear cell infiltration (along with hyperemia, i.e. dilatation of capillaries and small blood vessels).
C. In the left below (piglet no. 25). The lung tissue of an animal who developed typical UIP shows widespread mononuclear infiltration of interalveolar septa and peribronchial connective tissue (a lymphatic follicle like structure can be seen, magn. x100).
D. In the right below, the same piglet as above (no. 25). The mononuclear infiltrate in the peribronchial area consists mainly of lymphocytes along causes thickening of interalveolar septa (magn. x240).

biomedres-openaccess-journal-bjstr

Figure 3: Extensive interstitial pneumonia in PRRSV infection.
Note: Lungs of the piglet no. 40 show severe interstial pneumonitis: the infiltration of interalveolar septa by mononuclear cells (mainly lymphocytes) is so widespread that the original lung structure can be hardly seen. In addition, the abundant hyperemia along with extensive proliferation of connective tissue is clearly visible (magn. 220x).

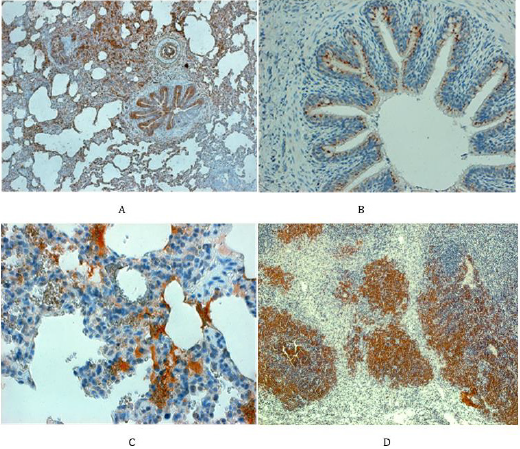
Staining with the anti-N antibody showed the presence of PRRSV antigen predominantly in the columnar ciliary epithelium lining the bronchial tree (Figure 4A). Details from such areas also demonstrated the presence of viral antigen in the cytoplasm of the small acinary mucous glands situated below the ciliary epithelium lining, namely in the connective tissue of bronchial wall (Figure 4B). The alveolar lining was rarely positive, though occasionally the type II alveolar cells could harbor the N-protein, mainly present in alveolar macrophages moving from the alveolar space across the thickened interalveolar septa into local lymphatic capillaries and/ or to the sinuses of regional lymph nodes (Figure 4C), where virus was finally deposited. Nevertheless, in some piglets the local lymph nodes did not stop the virus spread, which then might reach the spleen and/or liver via blood stream. The reticular cells of regional sinuses in spleen were found positive as well, and occasionally the antigen could be seen also in lymphatic follicles (Figure 4D).

biomedres-openaccess-journal-bjstr

Figure 4: Staining for N-antigen in the respiratory pathway and spleen
A. In the left above (piglet no. 34). The lungs of infected animals reveal overwhelming positive staining for N-protein, namely in the bronchial epithelium, in parabronchial mucinous glands and occasionally in the flat epithelium cells lining the aveoli (magn. 80x).
B. In the right above (piglet no. 12). The N-protein can be seen in the cytoplasm of ciliary epithelium cells lining the bronchi along with the negative goblet cells (magn. 120x).
C. In the left below (piglet no. 45). The N-protein can be seen in the cytoplasm of cells lining the alveolar wall and in mononuclear phagocytes which infiltrate the interalveolar septi (magn. 400x).
D. In the right below (animal no. 44): the spleen showing lymphatic follicles consisting mainly of lymphocytes positive for the N-protein (magn.x120).

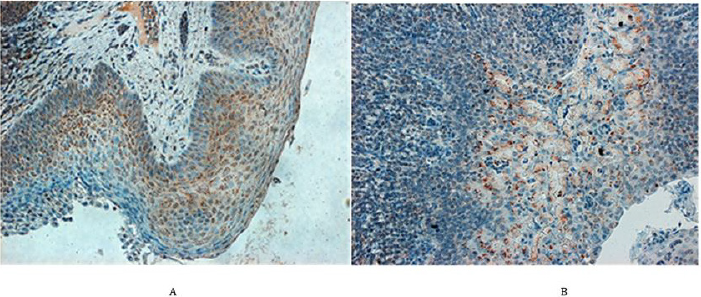
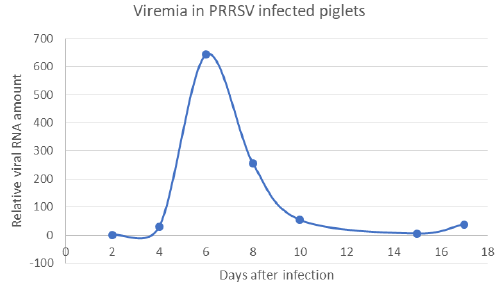
Outside of lung tissue, the N-protein of PRRSV was found especially in the non-hornified squamous epithelium of the pharyngeal area including that over tonsil (Figure 5A). Here the virus antigen occupied the deeper layers of stratified epithelium, namely the multiplying parabasal cells as well as those in the medium layer. The virus was also found in the salivary glands as documented in submandibular gland, which acinar cells harbored the N-antigen in their cytoplasm (Figure 5B). While the tonsils and/ or pharyngeal epithelium were involved relatively frequently, the presence of the virus in salivary glands acinar cell was relatively rare. Nevertheless, the real incidence of given antigen in the salivary glands was difficult to assess, since such tissue has appeared in the sections examined just by chance. The development of antibody response in comparison with lung lesions as detected by ELISA in serum samples is documented on Table 2. This shows that the virusspecific antibodies were rarely detected on day 11 post-infection but were frequently found on day 18. This may not be surprising and can be explained by the viremia (Figure 6), which peaked on day 6 post-infection, but was absent by day 10. Interestingly enough, on next day 11, the ELISA could not detect free serum antibodies, probably because they were bound to virus particles. However, the specific antibodies were clearly detected at later intervals (i.e. by day 18), when their levels in the serum increased.

biomedres-openaccess-journal-bjstr

Figure 5: N-protein in the pharyngeal area of PRRSV infected animals.
A. In the left (piglet no. 26). In the tonsillar squamous epithelium, the N-protein is expressed mainly wthin cytoplasm of actively growing cells of the suprabasal and intermedial layers including a few basal epithelium cells (magn. 220x) B. In the right (pig no. 13). N-protein can be seen in the acini of a submandibular salivary gland as well as in the marginal sinus of adjacent lymph node (magn. 220x).

biomedres-openaccess-journal-bjstr

Figure 6: Presence of vRNA in the serum of infected pigs (viremia has been detected on days 6 and 8 post-infection).

biomedres-openaccess-journal-bjstr

Table 2: The comparison of UIP with serological response.

Discussion

The PRR syndrome in piglets is characterized with high mortality, reproductive failure (late-term abortions and stillbirths, premature farrowing, mummified pigs in pregnant sows) and a severe respiratory disease (interstitial pneumonia). The disease occurring in the nursery and among growing/finishing piglets causes significant economic losses to the swine industry worldwide. The corresponding virus (PRRSV) replicates mainly in the porcine alveolar macrophages (PAMs) and dendritic cells (DCs) [20]. The virus also causes persistent infection eliciting antibody dependent enhancement (ADE) and occasional immunosuppression. Being a member of the family Arteriviridae, it belongs to the order Nidovirales together with the Coronaviridae and Roniviridae families [21]. PRRSV was originally divided into European type 1 and North American type 2 genotypes. Later on, the East European PRRSV isolates have been found to be of the European genotype but forming different subtypes. A novel virus, namely the Belarusian strain Lena, has been recently characterized as a highly pathogenic East European subtype 3, which differs from European subtype 1 Lelystad and North American US5 strains at genetic as well as antigenic levels [22].
Numerous results suggest that PRRSV may utilize multiple strategies of replication and spread in the infected pigs, including subversion of the host innate immune response, inducing an antiapoptotic and anti-inflammatory state as well as developing ADE. The PRRSV induced immunosuppression might mediate apoptosis of infected cells, which causes depletion of immune cells and induces an anti-inflammatory cytokine response due to which the host is unable to eradicate the primary infection. The initial antibodies do not confer protection and can even be harmful by mediating an antibody-dependent enhancement (ADE), since they can facilitate the virus entry of into targets cells in vitro. To characterize the humoral immune response direct enzyme-linked immunosorbent assays (ELISA) can be used including different mainly recombinant PRRSV antigens. For example, the kinetics of antibody responses directed against nonstructural virus coded proteins (nsp) can be analysed in pigs experimentally exposed to the virus [23]. In such case, high antibody reactivities especially against nsp1, nsp2, and nsp7 were noted. Among the latter, nsp7 recombinant proteinbased ELISA showed good sensitivity and specificity most suitable for diagnostic development especially for identification and differentiation of type 1 and type 2 PRRSV. Several non-structural proteins (such as nsp1, nsp2, nsp5, nsp7 nsp9, nsp10 and nsp11) have been implicated in the induction of IFN-γ and also in the development of the cell-mediated immune response [24]. On other hand, the induction of neutralizing antibodies (NAs) may be delayed and/or their levels may remain low, which is not only the problem of early diagnostic, but is also of importance regarding effective virus elimination. NAs may protect against disease if present in sufficient quantities before infection, but they do not seem to be essential for clearing virus in blood during the course of the infection. PRRSV is able to modulate innate responses, probably through the regulation of IFN-α and IL-10 responses [25].
As described, PRRSV replicates predominantly in the lung alveolar macrophages, can induce prolonged viremia, and cause persistent infections lasting for months after initial infection. PRRSV strongly modulates the host’s immune response and changes its gene expression. Studies showed that PRRSV inhibits type I interferons (IFN-β). Regarding cell-mediated responses, development of PRRSV-specific gamma interferon-secreting cells (IFN gamma-SC) and interleukin 4-secreting cells (IL4-SC) in PBMC was examined by ELISPOT assay. Using this technic, no IFN gamma-SC was detected until day 14 p.i., whereas for IL4-SC, such differences were not seen. Concurrently with the onset of viremia and the development of clinical signs, serum haptoglobin levels and interleukin 10 (IL10) in PRRSV-stimulated PBMC-culture supernatants increased significantly. These results are compatible with the model of pathogenesis in which the immune response does not fully control the outcome of infection [26].
The PRRSV replication and its spread in the body subverts the host innate immune response as well when high jacking its lipid metabolism and inducing an anti-apoptotic and anti-inflammatory state. The latter is indicated by suppressing the expression of serine proteinase inhibitor 2 (SPI 2), IFN-α, and down-regulation of the expression of pro-apoptotic genes such as B-cell lymphoma 2 (BCL-2) antagonist/killer (BAK) and the BCL-2 associated X (BAX). Whereas BAX resides predominantly in the cytosol, BAK is constitutively localized to the outer mitochondrial membrane; both form toxic mitochondrial pores in response to cellular stress. Furthermore, the APR-1, i.e., the Adenomatous polyposis coli (APC) protein which is a Wnt signaling component along with a microtubule-associated protein SARP3 (several ankyrin repeat protein 3), may be downregulated. Both were shown to interact with all isoforms of PP1 (protein phosphatase 1). Infections of N-PRRSV viruses resulted in fever and inflammatory response, as indicated by high expression of proinflammatory cytokines and chemokines, adhesion molecules, inflammatory enzymes and their receptors, such as IL-1β, IL8, SELL, ICAM, CCL2, CXCL9, CXCL10, B2M, proteasomes and cathepsins. This was compounded by cell death and elevated expression of NFKBIA, XAF1, GADD45A, perforin, granzymes, and cytochrome C, coupled with increased ROS-mediated oxidative stress, as indicated by up-regulated expression of cytochrome b245. Taken together, the N-PRRSV infection may have resulted in an excessive immune and inflammatory response that contributed to tissue damage [27].


For more Articles on: https://biomedres01.blogspot.com/

Friday, July 7, 2023

The Baseline of the Patient’s Cohort Undergoing Bariatric Surgery in Chile


The Baseline of the Patient’s Cohort Undergoing Bariatric Surgery in Chile

Introduction

The prevalence of obesity worldwide has reached pandemic levels in recent years, mainly due to profound changes in lifestyles, among which sedentary lifestyle and high calorie density diets stand out [1-3]. The Chilean population is not exempt from this reality, according to the latest data published by the Organization for Economic Cooperation and Development (OECD), 74% of the adult population in Chile are overweight or obese, making Chile the country of the OECD with the highest rate of obesity and overweight, above Mexico (72.5%) and the United States (71%) [4]. These data are reaffirmed with the 2016-2017 National Health Survey, which show that in Chile 42% of the adult population between 30 and 49 years of age are overweight, 31.2% are obese, and 3.2% of the population is morbidly obese [5]. Currently, obesity treatments include first-line lifestyle modification diet, physical activity, and behavioral therapy, and in some case pharmacotherapy [6]. However, only some patients achieve satisfactory weight loss or resolution of comorbidities associated with obesity with these conventional treatments. When patients do not respond favorably to these treatments, BC is considered. Strictly speaking, the term ‘bariatric surgery’ (BC) is applied to all surgical procedures that aim to reduce excess weight, and actually is considered as the most effective therapy available for significant and sustainable weight loss and control of obesity-related comorbidities in morbidly obese patients, improves the quality of life and reduces mortality in obese people [7-9].

Currently, it is estimated that in Chile there are about 500.000 morbidly obese people eventual candidates for BC. However, the National Health Fund (FONASA) provides treatment consistent in comprehensive care and BC to 400 people per year, an insufficient considering the morbidly obese people that currently exist in the country. The first published cases of BC in Chile date back to 1986 when González et al. described six jejunoileal shunts [10] and, in 1999 when the first horizontal gastroplasty in Roux-In-Y was described by Csendes, et al. [11], one year later, in the 2000, the first RYGB was performed at the public hospital San Juan de Dios Hospital of Curicó. BARCO is a cohort of obese patients operated for RYGB and SG procedures at the San Juan de Dios Hospital, in Curicó, Maule district, from January 2000 to May 2018. BARCO was created to support clinical, epidemiologic, and behavioral research to patients operated by BC in public regional health. This paper aims to report the baseline characteristics of BARCO´s patients, to provide a basic description of the sociodemographic, anthropometric measurements, principal comorbidities, mental health, lifestyle habits, clinical, and post-surgical complications of patients undergoing BC.

Materials and Methods

Data Collection

For data collection, a standard review file was created that included 46 variables with sociodemographic, clinical, mental health, main comorbidities diagnosed by a doctor, complications after the intervention, and lifestyle habits of patients undergoing BC. The data were collected through an exhaustive review of physical clinical records, two members of the BC team (one physical therapist and one nursing intern) were trained in data extraction from clinical records, to standardize the information collection method, while avoiding the reduction of systematic errors in their transcription. The information was entered into a database by two surgical interns who, in case of having any doubts regarding the values or data, reviewed the clinical file again for corroboration, in case of discrepancy the chief surgical team determined the inclusion or exclusion of the data. The compilation lasted 6 months.

Patients

biomedres-openaccess-journal-bjstr

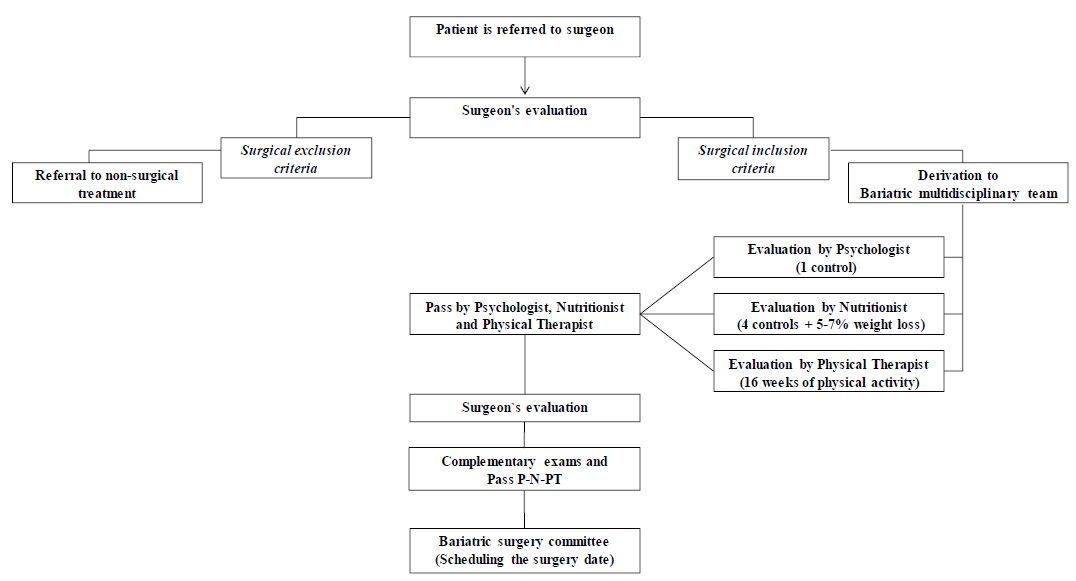
Figure 1: Diagram flow of the patients’ selection to bariatric surgery procedures. The patients’ selection to bariatric surgery procedures. Pass Psychologist = Pass P, Nutritionist = Pass N, Physical Therapist=Pass PT.

652 patients were operated on between January 1, 2000, to December 31, 2018, 3 adjustable gastric band, 5 deceased patients, and 19 patients whose clinical records were lost with the 2010 earthquake were excluded from this study. The remaining 625 patients, who were included, were older than 18 years with a BMI ≥ 35 kg / m2 in presence of at least one comorbidity, or BMI ≥ 40 kg / m2 without comorbidity, and who had undergone of RYGB or SG as the primary intervention. All patients had to be evaluated by the hospital’s BC multidisciplinary team, composed of bariatric surgeons, nurses, physical therapists, nutritionists, and psychologists (Figure 1).

Surgical Procedures Type

RYGB: For this procedure, a 5 cm gastric pouch with a 40-cc capacity was made with a 60 mm x 3.5 mm purple endo linear cutting stapler, between the 2nd and 3rd vessels of the lesser curvature, with 3 refills and 110 cm digestive loop and 150 cm biliopancreatic loop were used. SG: For this procedure, the greater curvature was dissected with a ligature from 4 cm proximal to the pylorus to the Hiss angle, and then the 36 F-calibration probe was installed under direct vision of the lesser curvature. Finally, an EndoGia 60 stapler was used for the section (5 purple loads). The Medtronic® kit was used for both procedures.

Variables

A database created included 46 variables referring to sociodemographic such as age, gender, occupation, and marital status: and the anthropometric measurements body weight, and BMI. The principal comorbidities like arterial hypertension, diabetes mellitus, insulin resistance, hypothyroidism, dyslipidemia, skeletal muscle diseases, obstructive sleep apnea, and gastroesophageal reflux, were included. Mental health including anxiety disorder, depression, bipolar disorder, and panic disorder were evaluated. Lifestyle habits such as alcohol, tobacco, and physical inactivity were also included. In the case of clinical parameters: pre-surgical exam results of upper gastrointestinal tract endoscopy and pulmonary evaluation by forced spirometry and rest EKG were evaluated. The number of RYGB and SG procedures between 2000 to 2018 years. Number of cholecystectomies during the surgical procedure and post-surgical complications. This study was approved by the Department of Teaching and Research of the San Juan de Dios Hospital of Curicó, complying with the criteria indicated in the Helsinki Declaration.

Data Analysis

Qualitative variables are presented as frequencies and percentages. The quantitative variables are presented as means, with standard deviations. It found that 34 were missing data, which were eliminated. The data observed mean in the case of continuous variables and use of the mode in the case of qualitative variables. To statistical analysis the data, the software SPSS version 2.4 was used.

Results

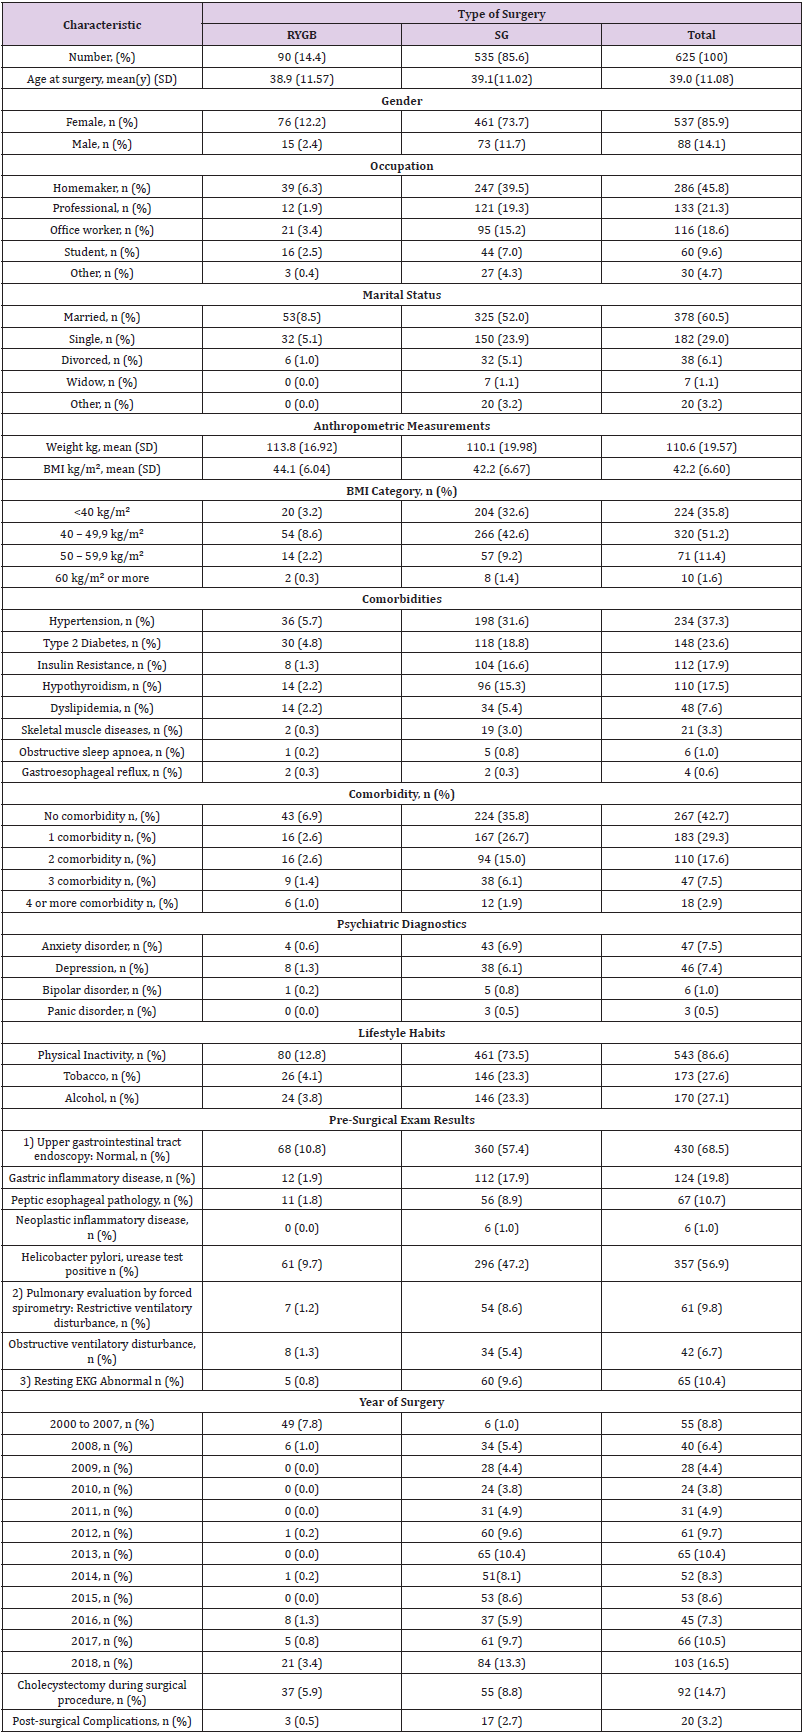
A total of 625 patients met the eligibility criteria of the study. SG was the most frequently reported procedure (85.6%) followed by RYGB (Table 1). Participants mean age was 39 years old and were predominantly female (85.9%). Most of the patients were homemakers (45.8%), professionals (21.3%), office workers (18.6%), 9.6% were students and 4.7% declared other kinds of occupation. Regarding marital status, 60.5% was married, 29% single, 6.1% divorced, 1.1% widows and 3.2% declared other. Regarding the anthropometric measurements, the mean of preoperative body weight was 110.6 kg and the mean of BMI was 42.2 kg / m². Most of the patients (87%) had a BMI ranged from <40 kg / m² to 49.9 kg / m², 11.4% 50 to 59.9 kg / m² and 1.6% have 60 kg / m² or more. The most prevalent comorbidities were hypertension (37.3%), type 2 diabetes (23.6%), insulin resistance (17.9%), hypothyroidism (17.5%), dyslipidemia (7.6%), the skeletal muscle diseases (3.3%), obstructive sleep apnoea (1%) and finally gastroesophageal reflux (0.6%). Regarding the total number of associated comorbidities, most of the patients (42.7%) did not present comorbidities at the time of surgery, 29.3% presented with one comorbidity, 17.6% presented with two comorbidities, 7.5% presented with three and 2.9% presented with four or more comorbidities.

biomedres-openaccess-journal-bjstr

Table 1: Baseline summary of BARCO patients.

Between the psychiatric diagnostic, the most prevalent were anxiety disorder (7.5%) and depression (7.4%), followed by bipolar disorder (1%) and panic disorder (0.5%). During the clinical interview, the patients declared about their lifestyle habits, 86.6% were sedentary, 27.6% smoked tobacco and 27.1% drank alcohol. The pre-surgical exam results indicated that 68.5% of patients presented with a normal upper gastrointestinal tract endoscopy, 19.8% gastric inflammatory pathology, 10.7% peptic esophageal pathology, and 1% presented neoplastic inflammatory disease. Notably, 56.9% of patients presented with Helicobacter pylori (H. pylori), positive urease test. Pulmonary evaluation by forced spirometry indicated that 9.8% presented with restrictive ventilatory disturbance and 6.7% obstructive ventilatory disturbance. Regarding the rest EKG, 10.4% of patients presented abnormal results.

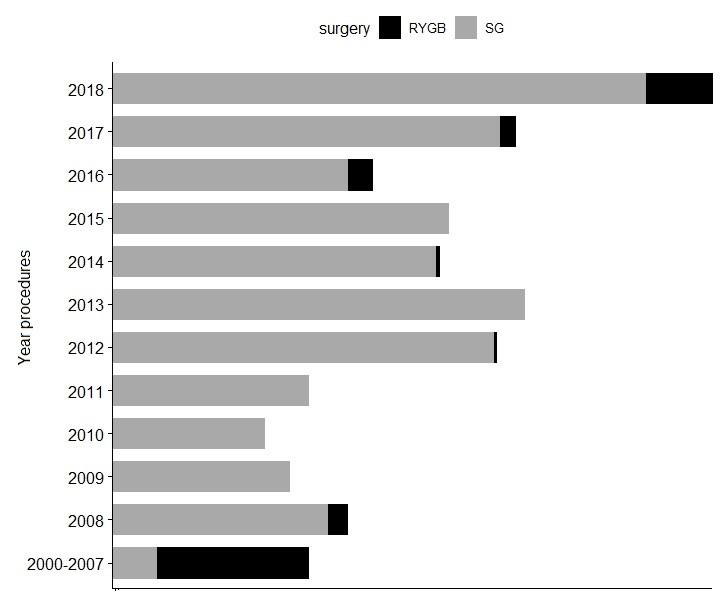
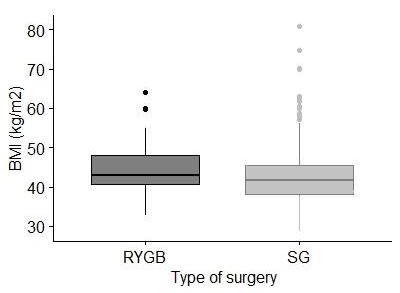
The number of bariatric procedures progressively increased, from 55 cases between 2000 and 2007, and over 100 cases in 2018. Regarding the type of surgery performed per year, between 2000 and 2007, RYGB was the most frequent procedure (49 of 55), however from 2008 to 2018, SG was the most reported procedure (528 of 568) used. During surgical procedures, 92 patients underwent a cholecystectomy, of which 55 were SG and 37 RYGB. Finally, the percentage of post-surgical complications was 3.2%, of which 2.7% corresponded to SG and 0.5% to RYGB. No patients died during the procedures (Table 1). The trends used from 2000 through 2018 are summarized by procedure types in Figure 2. The number of RYGB was higher compared to SG procedures between the years 2000 and 2008, and from 2008 onwards, the number of RYGB decreased and SG procedures had a significant increase. BMI distribution by bariatric procedure types is summarized in Figure 3. The mean BMI was 35 to 65 m/kg2 between both bariatric procedures, however, some patients operated with SG presented a BMI of over 60 m/kg2.

biomedres-openaccess-journal-bjstr

Figure 2: Bariatric surgery utilization trends over time, by procedures types.

Distribution of the number of bariatric surgery procedures from years 2000 to 2018. Roux-in-Y gastric bypass (RYGB) is show by the dark gray bars, and Sleeve gastrectomy (SG) by the light gray.

biomedres-openaccess-journal-bjstr

Figure 3: Body mass index by bariatric procedure types.

Box-and-whisker plots of body mass index (BMI) by surgery procedure types. Roux-in-Y gastric bypass (RYGB) is shown by the dark gray box and sleeve gastrectomy (SG) by the light gray box. The lines through the middle of the boxes are the means. The tops and bottoms of the boxes are the standard deviations.

Discussion

According to recent OECD data, Chile, a developing country, tops its list of obesity and overweight (74%), surpassing Mexico (72.5%) and the United States (71%) [4]. These data are reaffirmed with the latest National Health Survey, which shows an important increase of the obesity and morbid obesity from 21.9 % to 25.1 % and from 1.3 % to 2.3%, respectively, in the last 7 years [5,12]. Currently, it is estimated that in Chile there are about 500.000 morbidly obese people, who are eventual candidates for BC, an amount that according to projections is increasing. Although, the National Health Fund has annual coverage of 400 BC per year, it is insufficient considering the amount of morbidly obese people that currently exist in the country. It must be considered that, because BC is not routinely indicated for obese patients, the option of performing a SG versus RYGB was made according to a multidisciplinary team evaluation, considering comorbidities such as hypertension or type 2 diabetes. Effectively, as expected, SG patients had a higher prevalence of high-risk metabolic diseases as hypertension, type 2 diabetes, and insulin resistance. They also had higher rate of hypothyroidism, dyslipidemia and skeletal muscle diseases before surgery. As observed in this study, SG is the type of BC most performed followed by RYBG procedures, in public and private hospitals both in Chile [13] and in other countries [14,15].

However, in a recent article, Sun et al., indicated that RYGB was the BC type most frequently reported procedure in England followed by SG [16]. Despite these differences, it is important to note that both techniques are effective in the remission of the more prevalent comorbidities of the morbid obese, like type 2 diabetes, insulin resistance and hypertension [17,18]. In this study, it was observed that most of patients were female, which is consistent with other studies that point to a higher prevalence of surgical treatment for obesity among women [19]. This difference could be associated with the fact that in Chile, as well as in other countries such as the United States and Canada, the prevalence of obesity is higher in women than in men, and that women seek more health services compared to men, mainly because they have a greater concern for their health [20,21]. It can be assumed that this higher prevalence is due to the search for an ideal beauty and positive attributes, both associated with thinness, deriving from the many social demands that fall on women [22,23], although specific reasons for this disparity remain unclear. Considering the characteristics of the sample, it was observed that the majority ages of bariatric patients fluctuate between 39 to 46 years, are married or single, and BMI > 40 kg/m2, like other studies [13,21].

Most patients did not present comorbidities prior to surgery, and the prevalent comorbidities in patients are the same as those observed in other studies, type 2 diabetes, hypertension, insulin resistance, hypothyroidism, dyslipidemia and skeletal muscle diseases [21,24]. Interestingly, a higher prevalence of H.pylori (56%) diagnosed prior to surgery was observed, compared with similar studies that report 37.1% [25], and 22% [26] respectively. This difference may be due to the fact that the H. pylori infection is prevalent in 73% of the general Chilean population [27] and the social economic insecurity the patients face. However, the relationship between H.pylori and obesity is controversial, so further studies are needed in this area. It is known that obesity is a multifactorial disease that places individuals at risk for additional health compromising conditions such as biological, social consequences, psychological and psychopathology including depression and anxiety. In this study, it was observed that 93% of patients presented with psychiatric disorder including depression (47%) and anxiety (46%), higher than describe previously in another study of veteran women 60% (28% depression and 32% anxiety) [28].

One can also think that this higher prevalence is justified because most of patients were rural women, homemakers and sedentary. Therefore, it will be very interesting analyze the impact of BC procedure in these patients. Finally, none of the patients that died during the procedures were registered and only 3.2 % presented with immediate post-operative complications, which offers a satisfactory outcome when compared with other studies showing 5 to 10% [29]. These results obtained in the present study demonstrate that RYGB and SG BC procedures are feasible to be carried out in a public regional hospital with results comparable to those obtained in both public and private hospitals at the national and international levels. Although beyond the type of surgery applied, the therapeutic goals of surgery for morbid obesity are to improve quality of life and prolong life by counteracting the lifeshortening effect of obesity and its comorbidities, the future and ongoing investigations will provide evidence on the long-term benefits and risks of these most used bariatric procedures in current clinical practice.

This study presents some limitations, such as related to the external validity of our findings, because BARCO represents rural populations therefore, some results may not be applicable to residents of large urban areas. Here we report the baseline characteristics of BARCO´s patients, to provide a basic description of the sociodemographic, anthropometric measurements, principal comorbidities, mental health, lifestyle habits, clinical, and postsurgical complications of patients undergoing BC. In conclusion, given that BARCO is the largest cohort of the public health system patients operated of BC in Chile, these longitudinal data could be used to evaluate the effectiveness of the Chilean public policies related with the BC to treat the morbid obesity. Future and ongoing research will provide evidence on the long-term benefits, risks, and effectiveness of these bariatric procedures in reducing cardiometabolic morbidity, mortality related to obesity, and maintaining long-term weight loss. So, among the findings, the presence of Helicobacter pylori and the high prevalence of psychiatric disorders stand out as relevant factors for investigation in future studies.


For more Articles on: https://biomedres01.blogspot.com/

Thursday, July 6, 2023

Dynamics of P Under Redox Conditions in Rice in Tropical Soils


Dynamics of P Under Redox Conditions in Rice in Tropical Soils

Introduction

Rice is one of the main foods in the world, due to its nutritional content and because of the ease of handling and adaptation in different parts of the world, especially in tropical and subtropical conditions [1]. On the other hand, this crop is established under different types of management, depending on the genetic material to be managed, the type of tillage, agronomic management, fertilization plans and irrigation management [1]. Among the types of risks to be managed in rice cultivation, there is the condition of constant sheet or flooding, which has the advantage of properly managing weeds, avoiding stress in areas with high temperatures, reducing specific phytosanitary problems in each region; however, soil fertility is affected by the high and low availability of some nutrients [2,3]. Among the elements that are affected by its nutritional dynamics is Phosphorus (P), an element determined as a macronutrient and which is required to fulfill specific functions of the plant related to the production of energy (ATP) [4], in addition to the importance it has for the production of tropical agricultural systems [5].

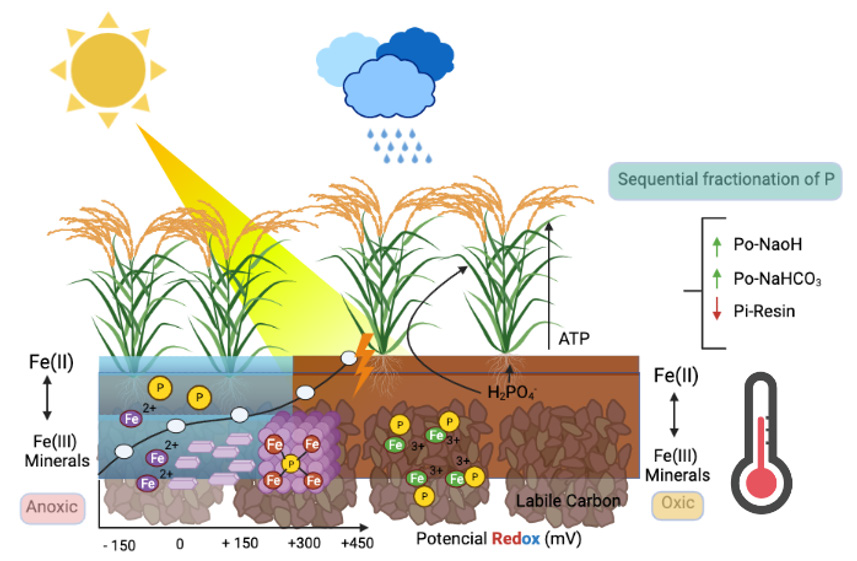
The behavior of this element is not the same when humidity is present at field capacity, as when flood irrigation is used in anoxic conditions, this, due to the fact that the concentrations of O2 in the soil are affected, the pH and pH are also affected. the dynamics of microorganisms that affect the available forms of P, as well as the concentration of elements such as Iron (Fe+2) that is found in the vast majority of tropical and subtropical soils in the form of minerals of high or low crystallinity. which directly influences the availability of P and the adsorption and desorption processes, in its Fe-P relationship, especially in acid soils where Fe is found in high concentrations and closely related to the oxidereduction conditions known as Redox conditions, which they are subject to the activity of electrons, pH and concentration of O2 in the soil; However, for this availability of P to exist, there are other parameters that must be present in the soil, such as high fertility defined by the cation exchange capacity (CEC), organic matter (OM) and especially dissolved organic carbon (DOC ) and a texture with high clay content [6,7], all this is described later as also in (Figure 1).

biomedres-openaccess-journal-bjstr

Figure 1: Dynamics of P in acidic soils in Redox processes in rice cultivation. Created with BioRender.com.

Relationship of pH and Eh in the availability of P

Is important to establish that flood periods do not generate immediate changes in pH, but can vary from a few to several weeks, among the factors that can establish changes in pH in flooded soils are: concentration of organic matter (dissolved organic carbon), Microbial activity, temperature, Fe concentration, ammonium accumulation, among other chemical properties of the soil [8,9]. Conditions such as pH and Eh are indirectly responsible for the release of P under reduced soil conditions [10,11]. After there is reduction in the soil by agronomic management such as flooding, regardless of the pH, which generally in tropical soils is very strongly acidic (<4.5) in soils of the orders Oxisol and ultisol, it has a tendency to rise until reaching the agronomic neutrality (6.5-6.8) [12,13], this is due to the fact that processes of reduction of MnO2 and Fe2O3 occur, to the production of OH- as a result of the mineralization of organic N to NH4 + through the process of the In the same way, the increase in pH can also be attributed to the rapid microbial mineralization of labile Carbon compounds (C), generating a rapid decarboxylation of organic anions and in addition to the ammonification as already mentioned above [14].

On the other hand, there is also a decrease in the redox potential (Eh), which is defined as a measure of the reduction state because it changes with the Oxidation / Reduction ratio; Eh is affected by the formation of complex ions and by pH [15]; It can be said that Eh decreases when the pH increases, therefore, the order of the compounds in which they are reduced in flood conditions in rice can be defined, which is described below: NO3 - = MnO2> Fe2O3 (Eh Low). In a soil with high Fe2O3 content such as oxisols, Eh remains an average of + 100 mV, however, in soils with little Fe2O3, Eh can range from -100 to -400 mV where the reduction of SO4 -2 to S-2 [16,17]. In the end, there is a correlation between pH and availability of P, studies carried out by [11] established that the increase in pH in acid soils (Oxisol and Ultisol), under flood conditions in rice, which indicated that these increases in pH, facilitated the Fe (III) reduction and associated P mobilization in the acid soils evaluated [18,19]

Dynamics of P and Fe Concentration

Lower Eh initial conditions in acidic soils such as oxisols [11], can result in a strong decrease in the sorption force of Fe-OP, leading to a strong increase in the P available in this type of soils [20,21]. In relation to this, it can be said that a reduction of Fe is more likely to occur at a slightly acidic pH, when the increase in pH is occurring in reducing environments [22]. It is important to bear in mind that potentially reducible Fe can be established, through methodologies such as the determination of Fe with Citrate-Ascorbate (FeCA), which indicates that the total concentrations of Fe (III) and recalcitrant Fe (Easily reducible) control the production. Fe (II) in acid soils such as Oxisols and Ultisols [11,23]. It is important to note that Fe (II) has a lower binding force for P than Fe (III) [24]; therefore soils with higher potentials to reduce Fe, an early increase and a higher bioavailability of P can be expected [22]. The reducing dissolution of crystalline Fe (FeCA, defines Fe and low crystallinity and potentially available and reducible Fe) can be catalyzed by a high concentration of Fe (II) [25,26], resulting in a higher initial availability of P in acid soils [11,27]. In short, the increase in the availability of P in flood conditions has to do with the reduction of ferric phosphates (Fe+3) to ferrous phosphates (Fe+2), to the release of P from insoluble components of Fe and Al and to a certain dissolution of Ca phosphates when there are high levels of CO2 in the soil solution (soils with alkaline pH). The release of P through these processes can take a few weeks after the flood. This initial flux of released P can be fixed on clay particles and Al hydroxides (AlOOH), and in some soils with high amounts of active Fe and Al it can still result in a reduction in the availability of P in the soil [28,29].

Organic Matter and P Concentration

Labile organic acids are more efficient to solubilize P from acidic soils, this because there is a greater solubility of Fe and Aluminum (Al) phosphates, with increasing pH and low Eh (Reference). Therefore, a decrease in Eh, followed by a reduction in Fe (III), can generate the release of P bound in Fe minerals; The reduction of Fe (III) and the corresponding accumulation of Fe (II), strongly depend on the labile mineralization of C and OM. Labile C can define the intensity of Fe (III) reduction because it is the main source of energy for microorganisms, in addition to being a strong electron donor [30]. These processes result in the production of Fe (II) but in the same way a desorption producing available P; therefore, higher OC and Fe (II) content in soils such as oxisols, generates a drastic decrease in Eh after immersion [11], which leads to a greater consumption of microbial O2 much faster, which can generate the release of large concentrations of P low binding energy (Reference). It is important to bear in mind that microbial mineralization with rapid activities due to the presence of labile C in acid soils can reduce P sorption, a specific adsorption analogous to phosphate ions [31] or by Fe and Al chelation [32].

Conclusion

It is important for the researcher, extension worker, professor in the area of agriculture, to understand the dynamics of P in systems where Redox processes are present, since for the producer it will serve as an orientation not to carry out high fertilization of phosphate fertilizers, which can lead to high processes of contamination by eutrophication, cost overruns, currently necessary due to the costs of fertilizers that have doubled and tripled their price in the market, in addition to the need to carry out calibrations in the determination of P in the soil, since in the tropics There is determination of P by the method of Bray II (Colombia), Mehlich 3 (Brazil - Minas Gerais), Resina (Brazil - São Paulo and Rio Grande do Sul), generating ambiguity by establishing non-standardized methodologies in various regions of the tropics and by Finally, in addition to values such as pH in the soil analysis, one should work on the fractionation of P as results in the soil analyzes for all The agricultural professional (Agronomist Engineer, Agroecologist Engineer, Agroforestry Engineer, etc.) who is the person in charge of the recommendation, with this, the forms of P, labile, moderately labile and nonlabile are determined to make a much clearer and more accurate recommendation.


For more Articles on: https://biomedres01.blogspot.com/

The Correlation between Altmetric Score and Citations in Pediatric Orthopaedic Journal Articles

  The Correlation between Altmetric Score and Citations in Pediatric Orthopaedic Journal Articles Introduction In scientific research, it is...